Show more
Show more
Show more
Paul M. Steinwald is a board-certified plastic surgeon serving the Center for Cosmetic Surgery with offices in Denver and Golden, Colorado. A highly accomplished surgeon with over 21 years of experience, Dr. Steinwald is known for his friendly, personalized ap


Asked By: Original481650
ANSWER
. . . for resolution of edema and scarring. If there was any ischemia (scabbing due to poor blood flow) you may have a thicker scar with is a bit more difficult to treat, but almost always these can be flattened out via a peripheral (edge of "areola") scar revision under local anesthesia only at 6-12 months post-op to determine what you really need, and when scars have matured/settled enough.
Asked By: SilentLucidity
ANSWER
. . . but your best option is probably a lateral browlift, from what you are describing. At your age you probably have an excellent hairline to hide scars (minimal if done endoscopically).
Asked By: chese0000
ANSWER
. . . via someone with experience in this matter, of course. Only limitation may be how much scar tissue is in the "recipient" zone for successful fat placement/take (but can almost always find donor fat!)
Asked By: jokirom618
ANSWER
. . . although swelling may be a limitation. The only two procedures I don't think go well together with respect to this would be lower eyelids and an infracturing rhinoplasty, which requires a splint. Would be selective with what matters most to you, however, and not try to "pack it all in"!
Asked By: dmmc2801
ANSWER
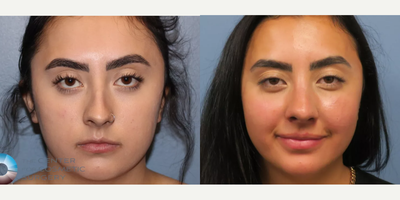
. . . but ultimately, I would address the rosacea with a dermatologist/skin care specialist to bring this under control; if successful, you may not need a rhinoplasty at all! But if "thicker" skin issues persist (at your young age), perhaps a refinement of the tip cartilage could help (although it doesn't appear you had this issue to begin with, so this appears to be a skin management issue more than anything . . . ) You have nice features, think carefully about more invasive procedures, at least early in your process.
Asked By: hema2
ANSWER
Ideally, you will be fully recovered (and rehabbed) following these joint replacements prior to any cosmetic surgery, but if the replacements were due to carrying excessive weight, ideally some of that weight will also be lost (during the rehab process) to put you in an optimal position at the time of your "mommy makeover" (as long as your weight also doesn't go "in the wrong direction" during the recovery process, of course . . . ) Ultimately your plastic surgeon can plan with you, but I'd guess you need to be (successfully) at least 6 months past the last joint replacement to be pursuing additional/elective surgery - best of luck, and take your time!
Asked By: Compassionate473834
ANSWER
Many considerations here, but the short answer is your breasts will always continue to age, but if you are quite large and are taken down to a C/D-range (yes, would recommend some degree of reduction - generally necessary anyway), you should never be anywhere close to where you area again (unless severe weight changes - and/or pregnancies - over time occur). Generally, (younger) age, post-operative support, ongoing fitness and good quality of skin (plus excellent surgical technique, and again, the size you are left with - smaller generally better) all should help you maintain your desired results. It is also quite possible to re-reduce/lift again in the future (many years down the road . . . )
Asked By: Fearless91667
ANSWER
Often times implants in this size range (which should achieve a 2-cup difference in someone with a relatively petite frame such as yours) should be able to be placed centered behind each nipple and without the creation of "symmastia", especially if placed under the muscle (but of course the surgeon needs to avoid over-dissection medially/towards the sternum). Attention to the base diameter of each implant relative to your anatomic measurements is also important (they shouldn't be too wide for your chest/ribcage). Hope this helps! (Attached is a photo of symmastia created elsewhere - with relatively small implants - that I corrected . . . not easy to do!)
Asked By: riri_rose
ANSWER
Often a significant weight loss involving an abdominal "apron", significant hip/flank skin, and loose buttock areas will benefit from a "lower body lift", started in the prone (face-down) position, after which the patient is repositioned supine, and the recontouring continues around the hips to address the abdomen as well. A concomitant upper arm lift would be reasonable if the surgeon and anesthesiologist believes it to be safe (generally these procedures alone would take at least 8 hours), but I would recommend against all 4 extremities being addressed in the same session, safety/time-wise, and in consideration of the limitations in mobility and self-care post-op.
Asked By: Celticangel1980
ANSWER
Often times an upper back-lift/bra-line scar doesn't need to connect in the midline/over the spine (unless truly redundant tissues there as well), but the scars need to be carried fairly anteriorly into the axillary/underarm areas to adequately address "bra rolls".
Dr. Paul M. Steinwald consistently delivers exceptional care and natural-looking results, earning high praise for his expertise, patience, and attentive communication. Patients highlight his ability to explain options clearly, make them feel confident in their decisions, and provide personalized, compassionate care throughout their surgical journey. Many note significant improvements in confidence, comfort, and quality of life following procedures, with smooth recoveries and minimal complications.